

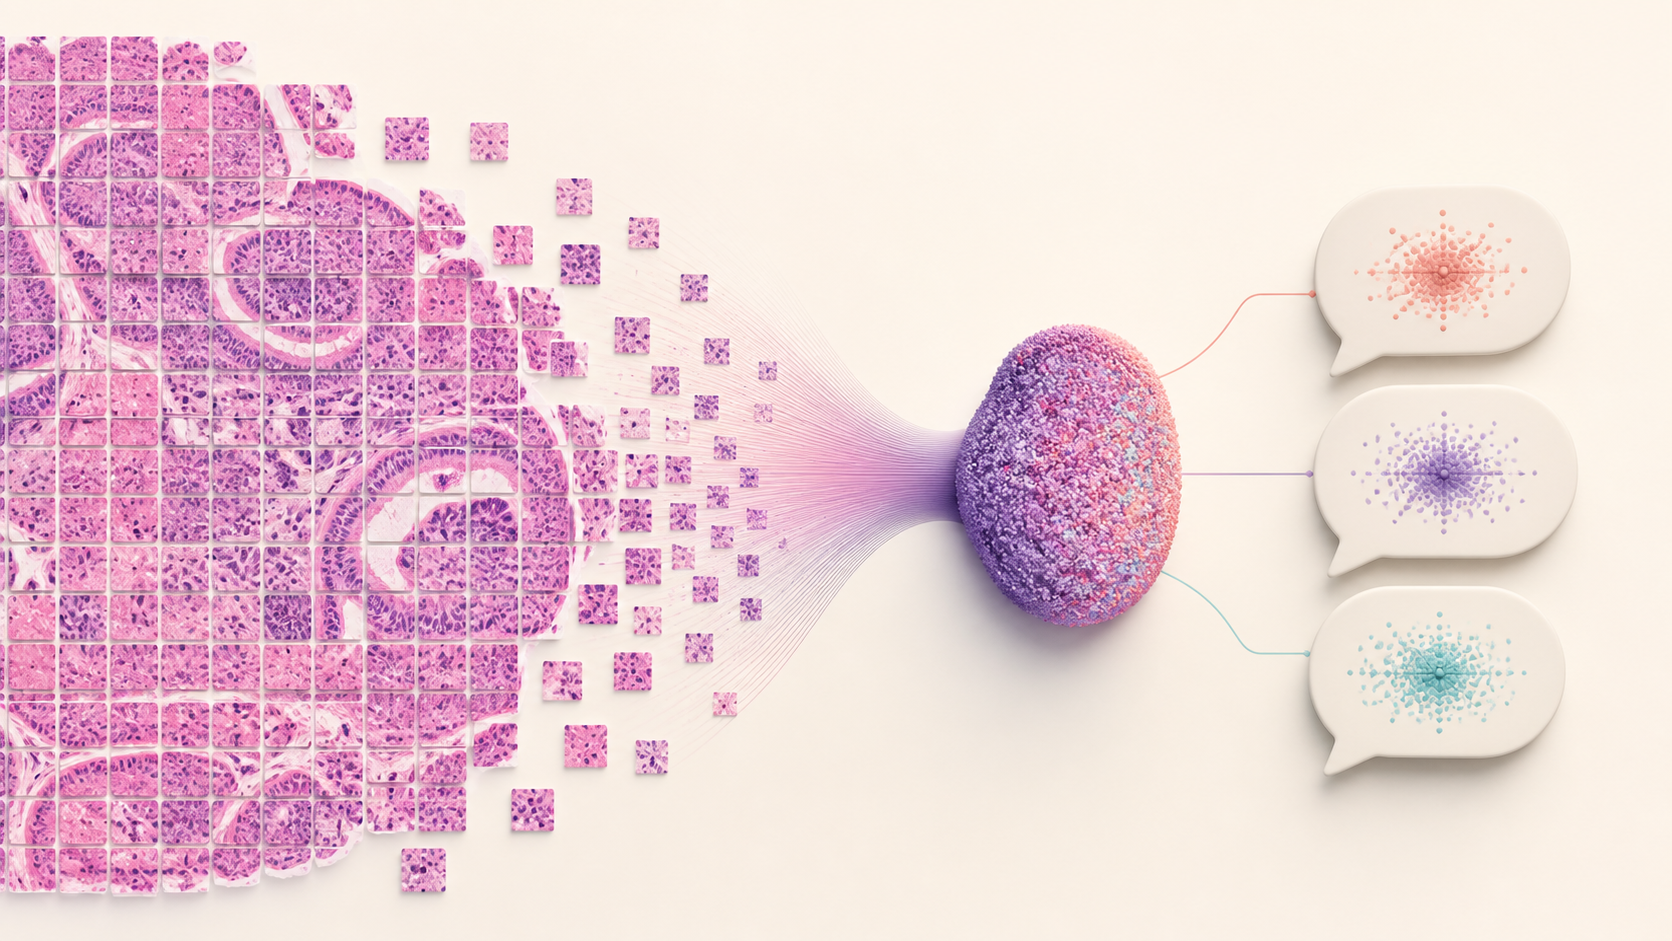
PRISM2 does more than classify pixels in a pathology slide. Built by Paige and Microsoft, the model aggregates thousands of tissue-tile representations and generates text in response to diagnostic questions. Its training connects whole-slide images with dialogue derived from clinical pathology reports.
The scale is substantial: 2.3 million whole-slide images and 685,507 reports from Memorial Sloan Kettering Cancer Center. GPT-4o converted those reports into question-and-answer pairs. The resulting system shows strong diagnostic and representation-learning results, but its synthetic supervision, single-institution data and architectural limits make external validation essential.
Joint visual and language training shapes the slide representation
PRISM2 is trained in two stages. First, a perceiver-based slide encoder combines Virchow2 tile embeddings into one slide-level vector. A contrastive objective aligns that vector with BioGPT report embeddings, while an autoregressive objective using Phi-3 Mini requires the representation to support text generation.
The combination addresses different weaknesses. Contrastive learning can produce embeddings suited to retrieval without supporting detailed generation. Autoregressive training can overfit to report language without learning transferable visual structure. PRISM2 trains both objectives against the same encoder output.
In the second stage, the slide encoder is frozen and a four-billion-parameter language model learns pathology dialogue. Training uses single-turn exchanges only, so the published system does not establish robust multi-turn clinical conversation.
The model exposes different representations for different tasks. Base embeddings come directly from the slide encoder and are recommended outside diagnosis-focused use cases. Diagnostic embeddings are extracted after the language model processes both slide information and a prompt. Survival analysis uses another separately fine-tuned representation.
Benchmarks show strength alongside important boundaries
PRISM2 reportedly matched or exceeded balanced accuracy from clinical-grade prostate and breast cancer products on their evaluation datasets, and outperformed Paige BLN on breast lymph-node classification without task-specific training. In pan-cancer detection, diagnostic embeddings reached 0.967 AUC versus 0.956 for base embeddings.
Rare-cancer performance fell to 0.957 AUC, which the paper attributes to limited examples. On colorectal-cancer recurrence-free survival, a fine-tuned PRISM2 encoder achieved a 0.809 concordance index compared with 0.773 for a specialist model trained on the same data.
Base embeddings performed better than diagnostic embeddings on biomarker tasks outside the report-dialogue distribution. That result reinforces the authors’ warning that the diagnosis-oriented representation should not be assumed best for every downstream use.
Dialogue templates improved prompt-based balanced accuracy from roughly 0.498 to 0.653. However, the question-answering dataset was 3.5 times larger than the earlier PRISM subset, and the paper attributes about half of the diagnostic gain to scale rather than architecture alone.
Synthetic dialogue and scanning assumptions require scrutiny
A pathologist reviewed 50 held-out specimens across ten tissue types. Errors in generated ground-truth questions were three percent across open-ended and multiple-choice formats, eight percent for diagnostic summaries and 18 percent for complementary yes-or-no questions. PRISM2’s own answer error rate was seven to 11 percent, with hallucinations and omissions dominating.
That review is informative but small relative to 685,507 source reports and 200,692 patients. Every dialogue example was generated with GPT-4o, so systematic synthetic errors could influence both training and evaluation.
PRISM2 also has no positional encoding across tiles, limiting built-in reasoning about spatial relationships. All slides were scanned at one resolution—0.5 microns per pixel—and Memorial Sloan Kettering supplied both training and evaluation scans. Different scanners, preparation practices and patient populations may shift performance.
Weights are available on Hugging Face, but the full training and inference pipeline depends on proprietary Paige and Microsoft infrastructure. Releasing weights therefore does not make the complete result independently reproducible.
PRISM2 is a compelling demonstration of diagnostic dialogue as supervision for pathology. Clinical teams should still test it on their own scanners, tissue mix and workflows, with pathologists reviewing errors. Strong internal benchmarks are a starting point; safe deployment requires proof that the representation transfers beyond the institution and assumptions that created it.









